
Congenital, Infantile & Juvenile Cataracts
A cataract is a clouding of the natural lens inside the eye. Although cataracts are most commonly associated with older adults, babies and children can develop cataracts too. And, pediatric cataracts are very different from adult cataracts.
Some babies are born with a cataract, called a congenital cataract. Others develop cataracts during infancy, childhood or adolescence. These may be called infantile, pediatric or juvenile cataracts.
In adults, cataract surgery is primarily about restoring vision that has become blurry. In a baby or young child, there is another critical concern: the brain is still learning how to see.
If a significant cataract prevents a clear image from reaching the developing visual system, the brain may not learn to use that eye normally. This can lead to severe amblyopia and permanent vision loss even if the cataract is eventually removed.
That is why pediatric cataract care requires expertise in much more than cataract surgery.
Pediatric cataract surgery is not adult cataract surgery performed on a smaller eye.
A baby’s eye is growing rapidly. Its tissues respond differently to surgery. The risk of amblyopia is much greater. Decisions about whether to implant an artificial lens can be very different. And successful treatment requires careful visual rehabilitation after the operation.
Our physicians manage that complete continuum of care—from deciding whether and when surgery is necessary through long-term visual development. For families, that means the physician treating the cataract also understands what must happen after the cataract is gone to give the child the best possible opportunity to develop useful vision.
What Is a Cataract?
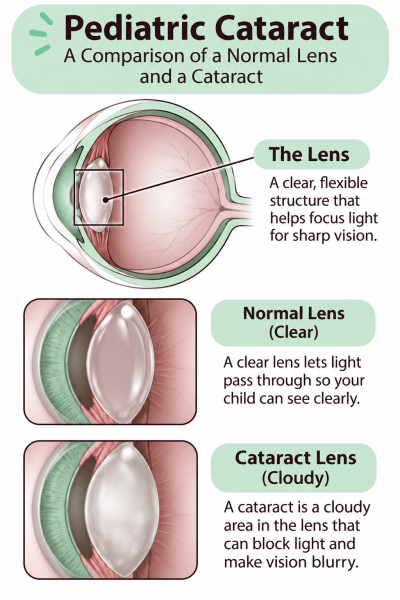
Behind the colored part of the eye is a normally clear structure called the lens. The lens focuses light onto the retina at the back of the eye. When the lens becomes cloudy, that cloudiness is called a cataract. Not all cataracts affect vision equally.
A tiny cataract located away from the center of the lens may have very little effect on what a child sees. A dense cataract directly in the visual axis can dramatically interfere with vision. In children, the effect of a cataract depends not only on its size and density but also on when it occurs during visual development. A cataract that significantly blocks vision during infancy can have a much greater effect than the same cataract developing after the visual system has matured.
What Is a Congenital Cataract?
A congenital cataract develops before birth and is present when a baby is born or becomes apparent shortly afterward. It may affect one eye or both eyes, and the appearance and severity can vary considerably.
Some congenital cataracts are discovered during a newborn examination when the pediatrician checks the baby’s red reflex. Others are first noticed by parents because the pupil looks unusual, an eye begins to drift or the baby does not seem to use one eye normally. Importantly, not every congenital cataract requires surgery. If a cataract is small, peripheral and not interfering with visual development, careful observation may be safer and more appropriate than operating.
The expertise is in determining which cataracts can safely be watched and which ones cannot.
What Are Infantile and Juvenile Cataracts?
Children are not always born with their cataracts. A cataract can develop during infancy, childhood or adolescence. These may be described as infantile, pediatric or juvenile cataracts. Some progress gradually and are discovered during a routine eye examination. Others cause noticeable changes in vision.
Whenever a new cataract is identified in a child, our pediatric ophthalmologists consider three important questions: Why did it develop? How much is it affecting vision? Is it likely to progress? Those answers help determine whether the child needs monitoring, additional medical evaluation or surgery.
Cataracts Associated With Uveitis and Other Medical Conditions
Not all pediatric cataracts are congenital. Chronic inflammation inside the eye, called uveitis, can cause cataract formation in children.
This can occur in children with conditions such as juvenile idiopathic arthritis as well as other inflammatory diseases. Treating these cataracts can be especially complex because the cataract and the underlying inflammation must both be considered. The timing of surgery, control of inflammation and postoperative management may all differ from the treatment of an uncomplicated congenital cataract.
What Causes Cataracts in Babies and Children?
There are many possible causes of childhood cataracts, and sometimes no specific cause is identified.
A cataract may result from abnormal development of the lens before birth, an inherited or genetic condition, another congenital abnormality of the eye, trauma, inflammation inside the eye, certain medications or a systemic or metabolic disorder. Some children have cataracts as an isolated eye condition and are otherwise completely healthy. Others may have associated eye findings or medical conditions that make the cataract only one part of a more complicated diagnosis.
This is one reason pediatric cataract evaluation extends beyond simply confirming that the lens is cloudy. Our physicians look carefully at the entire eye, the child’s medical history and the pattern of the cataract to determine whether additional evaluation is needed.
Why Are Cataracts So Different in Babies? This is one of the biggest differences between pediatric and adult cataracts. An adult who develops a cataract has already learned how to see. A newborn has not. During infancy and early childhood, the eyes and brain work together to build the visual pathways responsible for sight. The brain needs a reasonably clear image from each eye during this period. If a dense cataract blocks that image, the brain may begin relying on the other eye or may never develop normal visual connections from the affected eye. This can cause deprivation amblyopia, which can be profound.
Removing the cataract later does not always undo the loss of visual development that occurred while vision was obstructed. That is why a visually significant cataract in a baby can be time-sensitive. We are not simply treating a cloudy lens. We are protecting a developing visual system.
What Are the Signs of a Cataract in a Baby or Child?
A pediatric cataract may not produce obvious symptoms, particularly if it is small or affects only one eye.
A parent, pediatrician or eye-care provider may notice a white or gray appearance in the pupil, an abnormal red reflex, reduced vision, poor visual attention, an eye that begins crossing or drifting, nystagmus, squinting or increasing difficulty seeing. Older children may describe blurry vision, glare or one eye not seeing as well as the other. Young children often do not complain. If one eye sees normally, a child may simply rely on that eye and have no idea that vision is poor in the other.
That is why an abnormal red reflex, unusual pupil appearance or unexplained reduction in vision should be evaluated rather than waiting for the child to report a problem.
Do All Pediatric Cataracts Need Surgery?
No. Some cataracts are small enough or located far enough from the center of vision that they do not significantly interfere with visual development. These children may be followed carefully rather than operated on.
Our pediatric ophthalmologists consider the child’s age, cataract size and location, visual behavior, measured vision, progression over time and other findings within the eye when deciding whether surgery is necessary. The decision is individualized. For one child, the safest choice may be observation. For another, delaying treatment could reduce the eye’s long-term visual potential.
When Does a Baby or Child Need Cataract Surgery?
Surgery is generally recommended when the cataract is significantly interfering with vision or normal visual development. Timing can be especially important for a dense cataract affecting an infant.
A pediatric cataract surgeon considers whether one or both eyes are involved, the child’s age, how much of the visual axis is obstructed, whether strabismus or nystagmus is developing, how well the child appears to see and whether other abnormalities are present. There is no single age at which every pediatric cataract should be removed.
The goal is to intervene when the benefit to visual development outweighs the risks of surgery and anesthesia. That judgment requires experience with both pediatric cataract surgery and childhood visual development.
How Is Pediatric Cataract Surgery Different From Adult Cataract Surgery?
Pediatric cataract surgery requires specialized techniques because a child’s eye is not simply a smaller adult eye. The tissues of a child’s eye are more elastic and more reactive. Children are more prone to inflammation and to developing cloudiness along the visual pathway after surgery. Their eyes are also continuing to grow, which affects decisions about focusing power and intraocular lenses.
Depending on the child’s age and anatomy, surgery may involve removing the cloudy lens as well as part of the posterior lens capsule and a small amount of vitreous behind the lens. These additional steps may help keep the visual pathway clear after surgery. But performing the operation successfully is only the beginning. The surgeon must already be thinking about how the child will see tomorrow, next month and years from now.
Will My Child Receive an Artificial Lens?
Sometimes. An artificial lens placed inside the eye is called an intraocular lens, or IOL.
Many older children can receive an IOL at the time of cataract surgery. For very young infants, however, the decision is more complicated. A baby’s eye grows substantially during the first years of life, causing major changes in focusing power. Implanting an IOL into a very young eye also carries different risks than it does in an older child or adult. For infants, our pediatric cataract surgeons usually recommend removing the cataract without placing an IOL immediately.
The child is then considered aphakic and the focusing power of the missing lens is replaced with a specialized contact lens. An IOL may be considered later when the child is older. This is not an incomplete cataract surgery. For selected babies, aphakia is an intentional pediatric cataract treatment strategy.
What Is Aphakia?
Aphakia means that the eye does not have its natural lens. When a cataract is removed and no artificial lens is implanted at the same time, the eye is aphakic. Because the natural lens provides a significant amount of the eye’s focusing power, an aphakic eye is extremely out of focus without correction.
For an infant whose visual system is developing rapidly, that correction must begin promptly. Depending on the individual child, vision may be corrected with a specialized aphakic contact lens, aphakic glasses or, later, an intraocular lens.
Related: Aphakic Contact Lens Care
Children’s Eye Care Expertise in Aphakic Contact Lenses
Aphakic contact lens care is one of the areas where pediatric cataract treatment becomes especially specialized. These are not ordinary contact lenses worn for convenience. For a baby who has had a cataract removed, the contact lens may be essential for normal visual development.
Children’s Eye Care has extensive experience caring for infants and young children who require aphakic contact lenses after cataract surgery. Parents are taught how to insert and remove the lens, clean and handle it, recognize when a lens has been lost or displaced and know when irritation or another problem requires attention. The work does not stop once the family learns how to handle the lens. A baby’s eye grows rapidly, so the contact lens fit and prescription must be reassessed repeatedly. The power that is appropriate at one age may not remain appropriate as the child grows.
Our pediatric cataract team coordinates that optical care with the child’s visual development and amblyopia treatment. That allows surgery, optical correction and visual rehabilitation to remain connected instead of becoming separate pieces of care.
Cataract Surgery Is Only the Beginning
This may be the most important concept for parents to understand about pediatric cataracts. Removing the cataract creates a clearer pathway for vision. It does not automatically create normal vision.
After surgery, a child may still require an aphakic contact lens or glasses, frequent prescription changes, amblyopia treatment, patching, eye-alignment monitoring and surveillance for complications. For some babies, those treatments continue for years. This is why successful pediatric cataract care depends on much more than technically excellent surgery. The operation removes the obstacle. The years that follow help the brain learn to use the vision that surgery made possible.
Amblyopia After Pediatric Cataract Surgery
Amblyopia is one of the greatest threats to vision in children with cataracts, especially when only one eye is affected. Before surgery, the brain may have learned to rely almost entirely on the eye without the cataract. Removing the cataract gives the weaker eye a clearer image, but the brain may continue ignoring it. Patching the stronger eye may therefore be an important part of treatment after surgery.
Our pediatric ophthalmologists and orthoptists monitor the vision in each eye carefully and adjust amblyopia treatment as the child grows. The amount of patching required is individualized. Cataract surgery treats the lens. Amblyopia treatment treats the developing visual system.
Related: Amblyopia | Patching Help for Parents
Why Does My Child Need So Many Appointments After Cataract Surgery?
Because a child’s eyes continue changing long after the surgical incision has healed. During follow-up, we are not simply checking whether the eye looks good after surgery.
We are asking whether the child is receiving a clear image, whether the glasses or contact lens prescription is still correct, whether vision is developing, whether amblyopia treatment needs adjustment, whether eye alignment is changing and whether any complication is developing. In infancy, these changes can occur relatively quickly. As the child grows older, the examination also becomes more sophisticated because the child becomes capable of completing additional vision testing.
Pediatric cataract care is therefore long-term care, not a procedure followed by discharge.
Pediatric Cataracts and Strabismus
Children with cataracts may develop strabismus, particularly when one eye has experienced poorer vision than the other. Even after a cataract has been removed, the eyes may not immediately begin working together normally because the brain may already have learned to favor one eye. Some children improve as vision develops, while others may eventually require additional strabismus treatment.
Pediatric Cataracts and Nystagmus
When significant cataracts affect both eyes very early in life, normal visual development may be interrupted before the child has developed stable visual fixation. Some children develop nystagmus, an involuntary rhythmic movement of the eyes. Nystagmus can sometimes provide information about how early and severely vision was affected. Even when a cataract is successfully treated, nystagmus may persist because it developed during a critical period of visual development.
Pediatric Cataract Expertise at Children’s Eye Care
Pediatric cataracts sit at the intersection of complex eye surgery and childhood visual development.
Children’s Eye Care has specialized in pediatric ophthalmology in Metro Detroit since 1973, caring for babies and children with both common and some of the most complex childhood eye conditions. Our pediatric ophthalmologists manage the complete spectrum of pediatric cataract care, including congenital and infantile cataracts, juvenile cataracts, traumatic cataracts, inflammatory cataracts and cataracts associated with other developmental or medical conditions.
But the depth of our expertise is best demonstrated by what happens after the diagnosis. Our team follows children through the entire course of treatment: deciding when surgery is necessary, performing specialized pediatric cataract surgery, determining whether an intraocular lens or aphakic correction is most appropriate, fitting and managing aphakic contact lenses, treating amblyopia, monitoring visual development and eye alignment and providing long-term surveillance for glaucoma and other complications.
Our pediatric ophthalmologists work closely with orthoptists whose specialized expertise in childhood vision, amblyopia, strabismus and binocular development is particularly important in babies and young children who cannot explain what they see. Children’s Eye Care also participates in the education of ophthalmology residents and pediatric ophthalmology fellows, helping train the next generation of professionals who care for children with complex eye disease.
For a child with a cataract, our goal isn’t simply a successful operation. It is to give that child’s developing visual system the strongest opportunity for vision possible and to remain there for the years of care that may be required to achieve it.
The Unique Role of Orthoptists in Pediatric Cataract Care
Long-term pediatric cataract care depends on being able to answer a deceptively difficult question: How well is this child actually seeing?
That may be easy to ask but difficult to measure in a baby or toddler. Children’s Eye Care’s orthoptists have highly specialized training in evaluating visual development, eye alignment, eye movement and binocular vision in children. They are particularly skilled at measuring vision in babies, toddlers and young children who cannot reliably participate in a traditional adult eye examination. In children who have undergone cataract surgery, these measurements can be extremely important.
Our orthoptists work closely with our pediatric ophthalmologists to help determine whether vision is improving, whether one eye remains weaker, how the child is responding to patching and whether strabismus or nystagmus is developing. They also follow many of these children repeatedly over time, allowing subtle changes in visual development to be recognized.
Pediatric cataract care therefore takes place within a team whose daily work centers on children’s visual development – not simply the anatomy of the eye.
Frequently Asked Questions
SCHEDULE AN APPOINTMENT








